Pyloric stenosis typically presents between about 2 and 12 weeks of age with forceful, non-bilious vomiting after feeds and a hungry baby. The thickened muscle can sometimes be felt as an olive, but ultrasound is now the usual test. In emergency department studies, clinicians trained in point-of-care ultrasound have identified it accurately, though the studies are small. A formal scan or the paediatric surgeons confirm it.
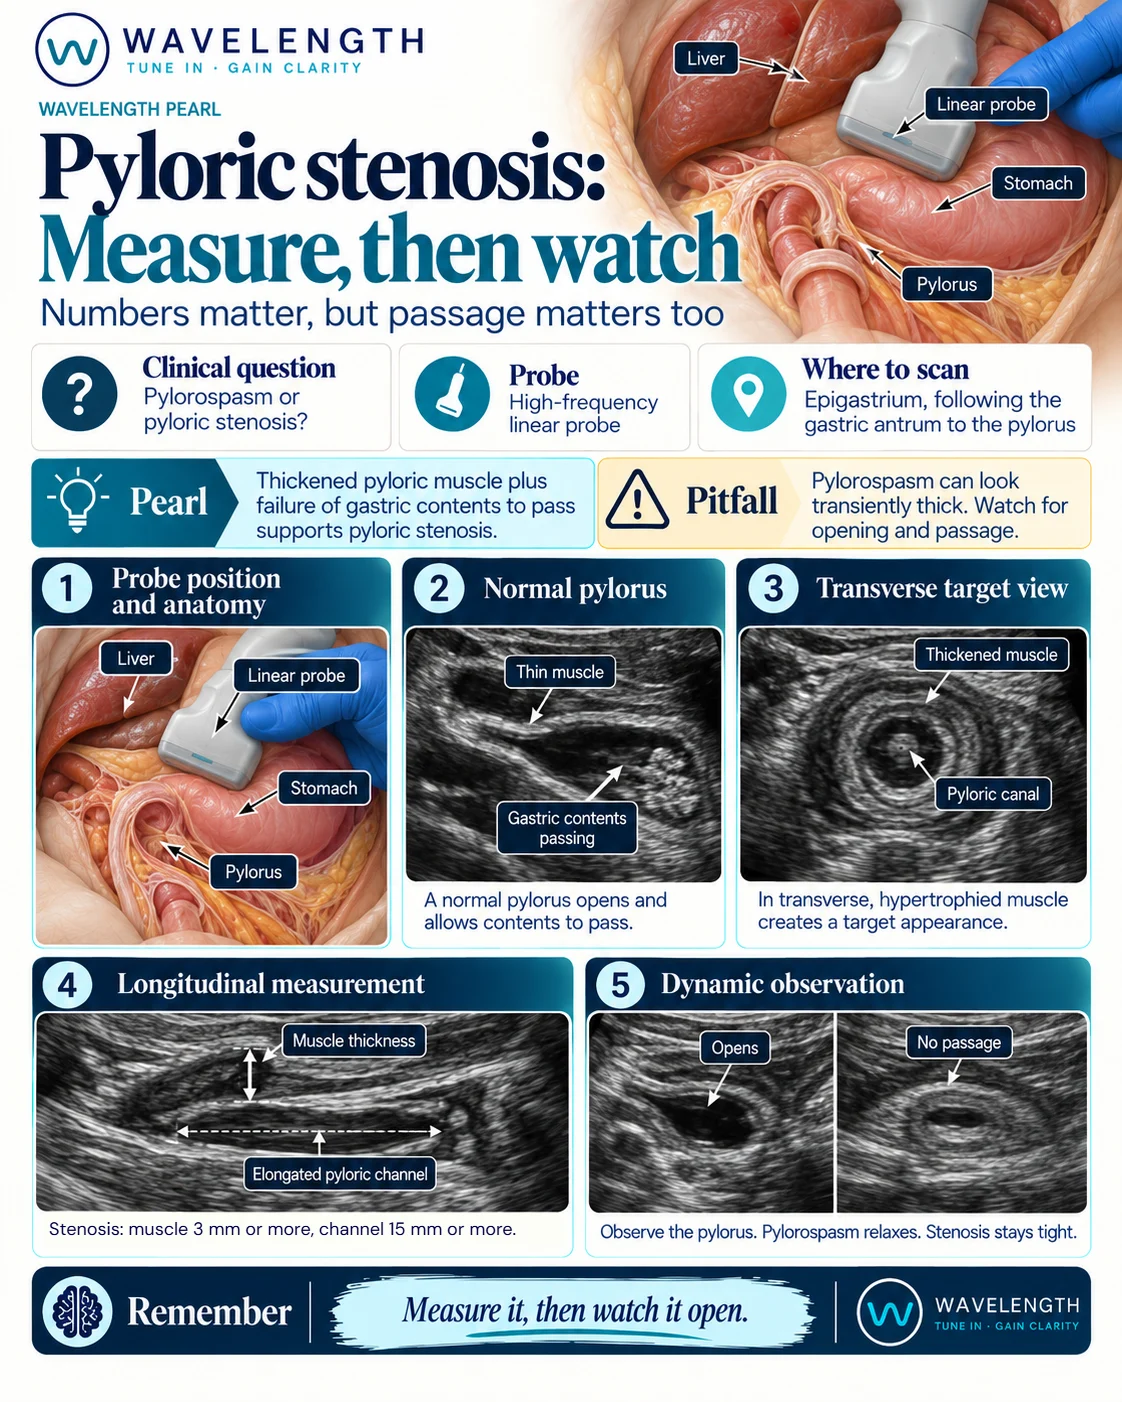
Scan images in the graphic are illustrations, not patient scans.
The scan
- Bilious (green) vomiting is not pyloric stenosis until proven otherwise: think of malrotation and call the surgeons now.
- Lay the baby supine, or turned slightly onto the right side so fluid fills the antrum. A small feed of milk or clear fluid helps.
- Use a high-frequency linear probe below the liver, to the right of the midline. Find the gallbladder, then the stomach, and follow the antrum to the pylorus.
- In short axis, look for the target: a thick dark ring of muscle around a bright centre.
- In long axis, measure the single muscle wall thickness and the length of the channel.
- Watch for several minutes. Does fluid pass through the pylorus?
Reading the view
- Normal: a thin muscle wall, a short channel, and fluid passing into the duodenum as the pylorus opens.
- Pyloric stenosis: a single muscle wall of 3 mm or more and a channel of about 15 mm or more, which stays closed while the stomach churns against it.
- Pylorospasm: the muscle looks thick for a while, then relaxes and lets fluid through. Measurements are often borderline.
Action
Refer to the paediatric surgeons. Check a blood gas and electrolytes: prolonged vomiting causes a low chloride, low potassium metabolic alkalosis, which must be corrected before surgery. Babies who are dehydrated, lethargic or bilious need urgent senior review.