A greater occipital nerve block is a quick, low-volume option for migraine and occipital headache with tenderness over the nerve. In a small emergency department trial, 4 of 13 patients with migraine which persisted after metoclopramide were headache-free 30 minutes after bilateral blocks, compared with none of 15 after a sham injection. The trial stopped early, so treat this as promising rather than proven.
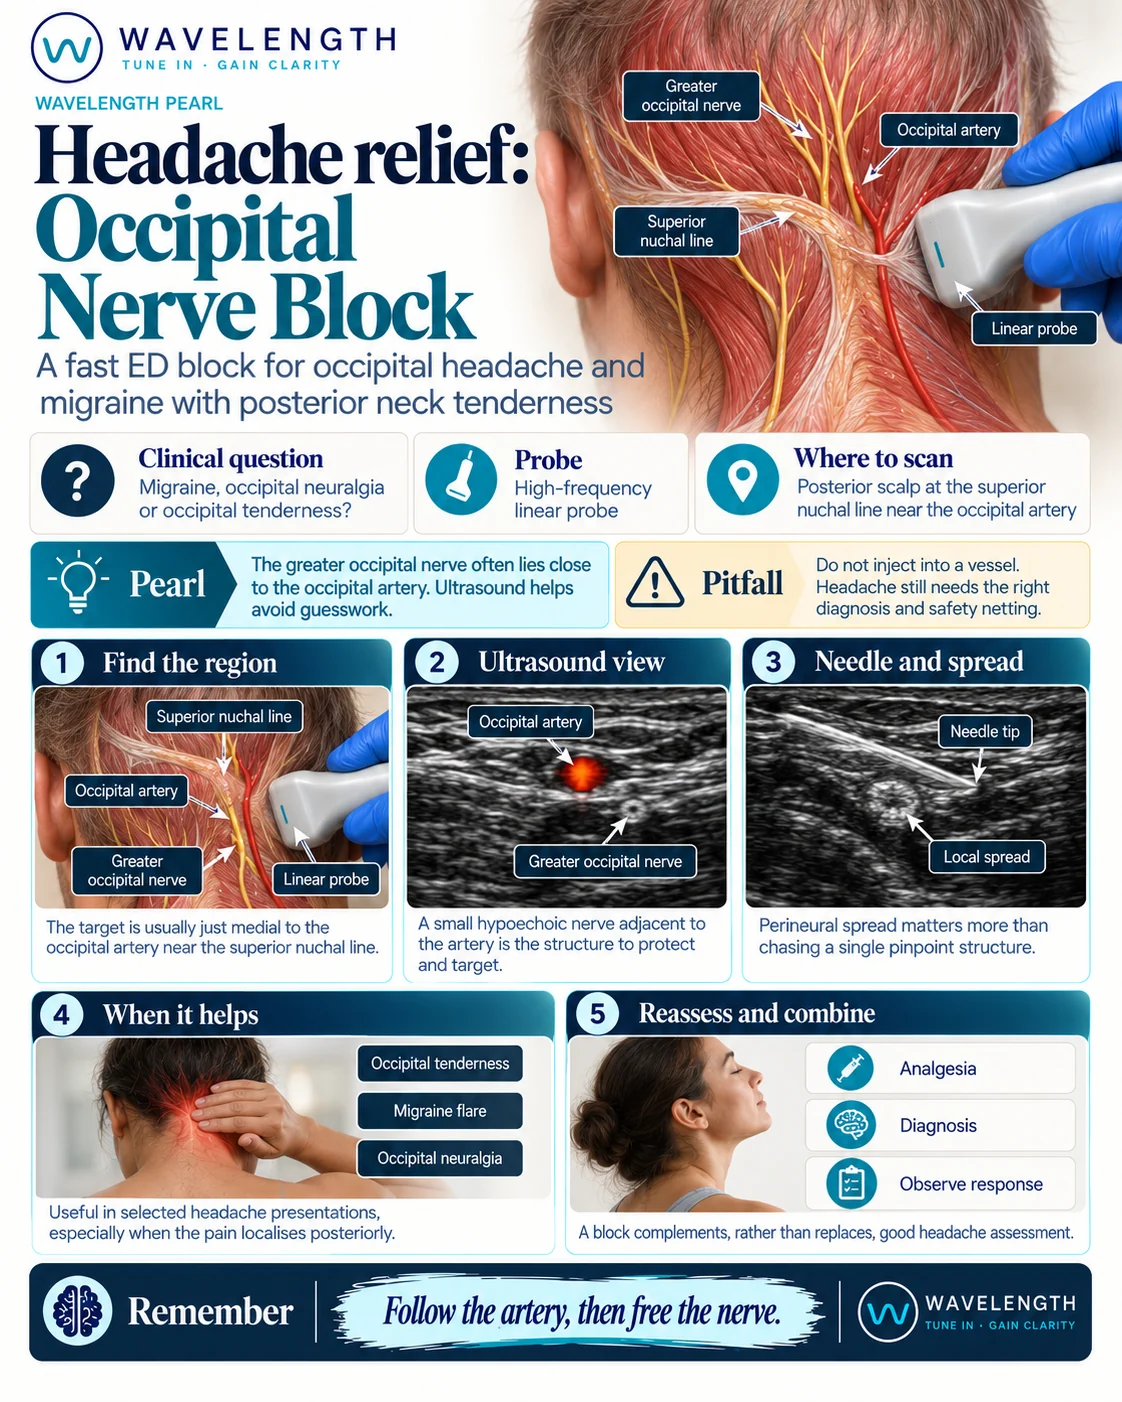
Scan images in the graphic are illustrations, not patient scans.
Before you block
- Take a headache history and examine the patient. Thunderclap onset, new neurology, fever, neck stiffness, papilloedema, pregnancy or a first severe headache over 50 need investigation, not a block.
- Explain the procedure and its risks, and record consent.
- Check allergies and anticoagulants, and calculate a safe local anaesthetic dose.
The scan
- Sit the patient up, leaning forward with the neck slightly flexed, or lie them prone.
- Use the high-frequency linear probe, transverse, on the back of the head at the level of the superior nuchal line, about a third of the way from the occipital protuberance to the mastoid.
- Switch on colour Doppler and find the pulsating occipital artery.
- Look for the nerve beside it, usually medial to the artery: a small, round, dark structure with a bright rim.
- Insert the needle in plane, aspirate, and inject a small volume around the nerve, watching the spread.
Experienced operators also block the nerve lower down, at the level of C2, where it runs between obliquus capitis inferior and semispinalis capitis.
Reading the view
- Artery. Round, dark and pulsatile, with flow on colour Doppler.
- Nerve. A smaller dark oval with a bright rim, next to the artery, with no flow.
- Good spread. Fluid surrounds the nerve. Chasing a pinpoint target matters less than a ring of fluid in the right plane.